
Blog
Progressive Lenses and Dizziness: Could Your Patient’s Glasses Be Affecting Their Balance?

A 72-year-old patient comes to see you because she continues to feel unsteady despite recovering well from a vestibular disorder. Her vestibular examination is improving. Her strength is good. She walks reasonably well in the clinic.
But she tells you something interesting:
“I feel much worse in the grocery store, when I turn my head while walking, and especially when I look down going downstairs.”
We often think about the vestibular, neurological and musculoskeletal reasons for these symptoms. But there is another question worth asking:
What type of glasses is she wearing?
For patients experiencing dizziness, imbalance or motion sensitivity, progressive lenses may be an overlooked fact...
Persistent Concussion Symptoms: Are We Assessing Everything the Neck Actually Does?

An athlete is four weeks post-concussion.
Their recovery has plateaued. They continue to experience headaches, dizziness, imbalance, visual complaints, or difficulty progressing back to sport.
At this point, it is easy to assume the remaining symptoms are still coming from the brain.
But here's a question worth asking:
What are the chances the neck was injured too?
The forces involved in concussion do not necessarily affect the brain in isolation. Rapid acceleration, deceleration, and rotation of the head also place considerable demands on the cervical spine.
If enough force was transmitted to produce a concussion, is it reasonable to assume the neck escaped injury?
The challenge is t...
Acute Vestibular Syndrome: When Should You Perform the HINTS+ Examination?
You have a patient sitting in front of you with acute dizziness.
Should you perform the HINTS+ examination?
The answer depends on one critical question:
Does your patient have Acute Vestibular Syndrome (AVS)?
One of the most common mistakes we see is clinicians performing HINTS+ on patients who do not meet the criteria for Acute Vestibular Syndrome. The examination was developed and validated in a very specific patient population. When applied outside of that population, the evidence demonstrating HINTS+ to be more sensitive than early MRI no longer applies.
Before discussing HINTS+, let's first answer the more important question.
What Is Acute Vestibular Syndrome?
Acute Vestibul...
Idiopathic Intracranial Hypertension: A Clinician's Guide to Diagnosis & Management
Every vestibular therapist has encountered the patient whose dizziness simply doesn't fit.
Vestibular testing is largely unremarkable, yet the patient reports persistent headaches, motion sensitivity, visual complaints, and imbalance. They may have already been diagnosed with vestibular migraine, Persistent Postural-Perceptual Dizziness (PPPD), cervicogenic dizziness, or even anxiety, but something about the presentation feels atypical.
One diagnosis that deserves a place on the differential is Idiopathic Intracranial Hypertension (IIH).
Although IIH is relatively uncommon, recognizing it is critically important because delayed diagnosis can result in permanent visual loss. As vestibular...
Can Convergence Exercises Cause Harm After Concussion?
What the latest evidence says about Brock String therapy, convergence insufficiency, and spasm of the near reflex
A lot of us have been taught convergence exercises such as Brock String and pencil push-ups at courses related to concussion and vestibular rehabilitation.
Recently, however, concerns have emerged suggesting these exercises may worsen visual dysfunction or even cause permanent damage.
Given this, I thought it would be prudent to revisit the literature and see what the evidence actually says.
The short answer?
Current evidence does not support permanent structural visual or neurological harm from convergence exercises.
In fact, the newest concussion-specific research suggest...
Atypical BPPV: Understanding Posterior Canal BPPV Variants

Most clinicians are comfortable treating classic posterior canal BPPV.
Horizontal Canal BPPV Apogeotropic: Rethinking Treatment

Most of us were taught and continue to be taught that sustained apogeotropic nystagmus indicates cupulolithiasis when the lateral canal is involved.
But what if that’s not necessarily true?
In this blog I want to take you on a brief journey and challenge what we’ve traditionally been taught about these presentations.
Understanding Horizontal Canal BPPV
I think that we can all agree that when positional testing (i.e. Supine Roll, Dix-Hallpike, Sidelying, Bow & Lean) produces horizontal nystagmus, we are most often dealing with horizontal canal BPPV. It’s important to remember that positional nystagmus can also be seen with conditions such as light cupula or central causes.
The classic p...
Creatine for Concussion Recovery: What Does the Evidence Actually Say?

Interest in creatine for concussion recovery continues to grow among clinicians, athletes, and patients looking for strategies to support brain healing. As providers managing concussion, prevention remains foundational. When injury occurs, however, the focus shifts to a key question:
What physiologic environment best supports neurologic recovery?
Evidence-based concussion management emphasizes education, graded return to activity, sleep optimization, autonomic regulation, and targeted rehabilitation. Increasingly, patients also ask about supplements. As a result, clinicians need clarity on whether creatine for concussion recovery is biologically plausible, clinically useful, or still theor...
Pupillary Assessment With Infrared Goggles: A Vestibular Therapist’s Guide
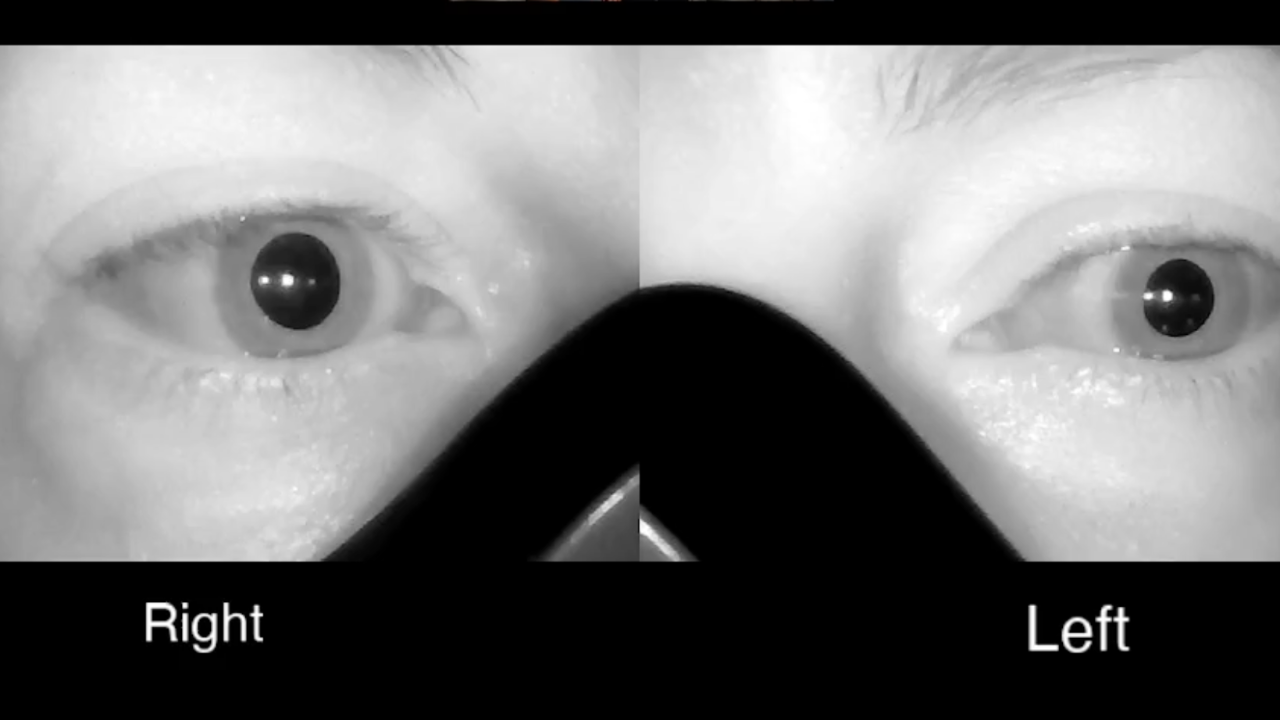
Many vestibular clinicians capture eye movements routinely, but what if your infrared goggles were revealing clues about autonomic nervous system function, not just nystagmus?
A chiropractor friend of mine recently sent me a recording of a patient with atypical positional nystagmus, one of those cases where the eye movements do not follow the usual “BPPV patterns.” We worked through the positional findings and landed on a reasonable clinical interpretation and plan.
My friend who shared the recording is an exceptionally sharp clinician, currently working on his PhD, with deep expertise in the autonomic nervous system. What really caught my attention was his notes stating:
Cranial Nerve...
Lateral Canal Light Cupula: A Case-Based Clinical Reasoning Journey
Lateral canal light cupula can closely mimic lateral canal BPPV, yet it often fails to respond to canalith repositioning or liberatory maneuvers. This case study explores diagnostic features, migraine susceptibility, and clinical reasoning that supports conservative management and an excellent prognosis.
Understanding Light Cupula in the Lateral Canal
Benign paroxysmal positional vertigo (BPPV) is commonly conceptualized as a mechanical disorder driven by free-floating otoconia. In most cases, canalith repositioning maneuvers are highly effective. However, not all gravity-dependent positional nystagmus reflects classic canalithiasis.
Light cupula of the lateral canal represents a cupula-d...
Author

Kregg Ochitwa
Physical Therapist I Vestibular Therapist I Clinic Owner
Categories
All Categories